

A Race Against Time: Collaborative Emergency and CTVS-Led Endovascular Repair in Traumatic Aortic Transection with Polytrauma

Published by IFEMAdmin
August 29, 2026
A case report highlighting the rapid, multidisciplinary management of a life-threatening traumatic aortic transection in a patient with polytrauma, from early recognition and stabilisation to emergency endovascular repair and recovery.
Authors: Dr Abhijeet Devidas Kayarkar, Dr Chiranjeevi, Dr Dheeraj Nair, Dr Neerav Bansal, Dr Pramod Sharma, Dr Tarun Sikarwar
Department of Emergency Medicine, Max Super Speciality Hospital, Vaishali, India
Introduction
Blunt traumatic aortic injury is a time-critical vascular emergency accounting for approximately 20% of deaths following high-speed motor vehicle collisions [1]. It typically occurs at the aortic isthmus, just distal to the left subclavian artery, where the fixed and mobile segments of the aorta meet [2]. While the majority of patients succumb at the scene, those who reach the hospital alive have a limited window for diagnosis and intervention.
The emergency physician’s role is pivotal—ensuring early recognition, stabilisation, and activation of a coordinated trauma response involving the CTVS team for definitive repair [3]. With the advent of thoracic endovascular aortic repair (TEVAR), outcomes in blunt traumatic aortic injury have improved substantially compared to open surgical approaches, reducing mortality, morbidity, and recovery time [4–6].
This case exemplifies outstanding teamwork between Emergency Medicine and CTVS teams, showcasing how time-sensitive decision-making and multidisciplinary precision led to survival from a near-fatal injury.
Case Presentation
Initial Presentation and Assessment
A 38-year-old male was brought to the emergency department following a high-energy two-wheeler accident. On arrival, he was conscious and oriented (GCS 15/15) and haemodynamically stable.
Primary survey: No airway compromise, equal bilateral breath sounds, no external bleeding.
Secondary survey: Scalp abrasions, no abdominal tenderness, and right thigh deformity with shortening, suggesting femoral fracture.
The emergency physician initiated ATLS-based stabilisation, including oxygen supplementation, fluid resuscitation and blood transfusion.
Imaging and Diagnostic Findings
Contrast-enhanced CT (CECT) polytrauma revealed:
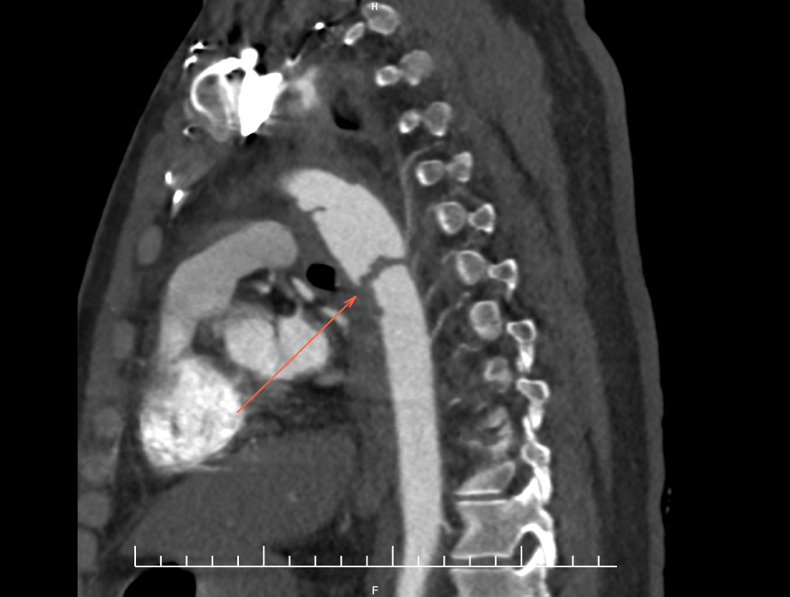
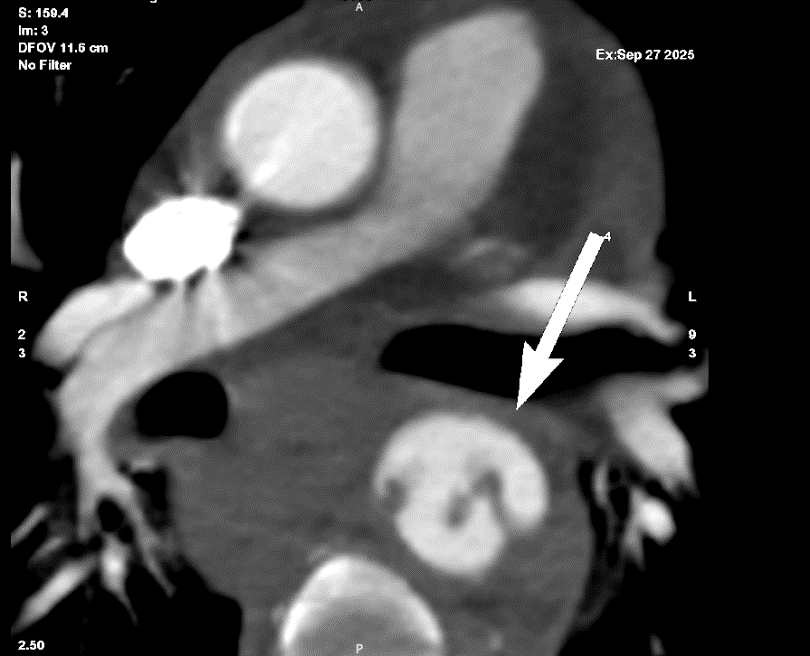
- Aorta: Acute transection with limited dissection 4–6 cm distal to the left subclavian artery, forming a contained pseudoaneurysm with mediastinal haematoma compressing the oesophagus.
- Thoracic findings: Mild haemopericardium, bilateral pulmonary contusions, and thrombus extending to the pulmonary artery bifurcation.
- Brain: Small bilateral frontal contusions without mass effect.
- Musculoskeletal: Comminuted right femoral shaft fracture with posterior displacement.
Emergency and Surgical Management
Recognising the imminent risk of rupture, the Emergency Medicine team activated the multidisciplinary trauma protocol, alerting CTVS, Orthopaedics and Neurosurgery. After stabilisation, the patient was shifted to the hybrid operating suite for emergency TEVAR on 27 September 2025.
Procedure Details
- Access: Right femoral artery open exposure and left femoral artery catheterisation.
- Device: Medtronic Endurant stent graft (24/24/100 mm).
- Result: Successful sealing of the pseudoaneurysm; no endoleak; haemodynamics normalised intraoperatively.
The patient was extubated the next morning and remained stable under intensive monitoring. Neurosurgical management of frontal contusions was conservative. After stabilisation, ORIF with intramedullary nailing of the right femur was performed by the Orthopaedics team.
Within 30 hours post-ORIF, the patient developed irritability and desaturation. CT pulmonary angiography (CTPA) ruled out pulmonary embolism; fat embolism syndrome was diagnosed clinically. Conservative management with oxygen, fluids and corticosteroids led to steady improvement. The patient was discharged fully alert, haemodynamically stable, and ambulating with assistance.
Discussion
Traumatic aortic transection represents a critical challenge in emergency trauma care. Mortality remains high without rapid diagnosis and intervention [5]. In this case, early recognition by the emergency physician, guided by mechanism-based suspicion, was pivotal. Activation of the hybrid trauma response ensured simultaneous stabilisation and endovascular repair within hours, demonstrating exemplary Emergency–CTVS synergy.
Endovascular repair (TEVAR) has now replaced open repair as the standard of care for descending thoracic aortic injuries due to its reduced risk of bleeding, paraplegia, and mortality [6–8]. The multidisciplinary collaboration extended beyond surgery—orthopaedic, neurosurgical, and internal medicine teams coordinated seamlessly, allowing safe sequential management of injuries. Continuous postoperative vigilance for complications like fat embolism was crucial to overall recovery [9].
This case exemplifies modern trauma management principles—speed, system activation, and multidisciplinary precision—that transform outcomes in previously unsurvivable injuries.
Conclusion
This case demonstrates that timely suspicion, rapid imaging, and coordinated multidisciplinary intervention—led by Emergency Medicine and executed by the CTVS team—can convert a catastrophic aortic transection into a survival success. The keys to outcome were time, teamwork, technical excellence and leadership.
References
- Fabian TC, Richardson JD, Croce MA, et al. Prospective study of blunt aortic injury: multicenter trial of the American Association for the Surgery of Trauma. J Trauma. 1997;42(3):374–380.
- Parmley LF, Mattingly TW, Manion WC, et al. Nonpenetrating traumatic injury of the aorta. Circulation. 1958;17(6):1086–1101.
- Azizzadeh A, Keyhani K, Miller CC III, et al. Blunt traumatic aortic injury: initial experience with endovascular repair. J Vasc Surg. 2009;49(6):1403–1408.
- Riambau V, et al. Management of Descending Thoracic Aorta Diseases: ESVS Guidelines. Eur J Vasc Endovasc Surg. 2017;53(1):4–52.
- Walls RM, Hockberger RS, Gausche-Hill M. Rosen’s Emergency Medicine: Concepts and Clinical Practice. 10th ed. Elsevier; 2023.
- Xenos ES, Abedi NN, Davenport DL, et al. Meta-analysis of endovascular vs open repair for traumatic descending thoracic aortic rupture. J Vasc Surg. 2008;48(5):1343–1351.
- Jonker FH, Giacovelli JK, Muhs BE, et al. Endovascular treatment of traumatic aortic injury improves early survival. J Vasc Surg. 2010;52(3):551–556.
- Clouse WD, Rasmussen TE, Pweck MA, et al. Intraoperative findings and management of blunt thoracic aortic injury: evolution of surgical techniques. Ann Thorac Surg. 2004;78(4):1237–1243.
- Bulger EM, Nathens AB, Rivara FP, et al. Management of severe blunt trauma. N Engl J Med. 2020;383(18):1693–1702.